Skip to content
Dr. Khalid AletaibiConservative Dentistry · Dubai

BIOMIMETIC RESTORATIONS

Crowns, only when there's no smaller answer.

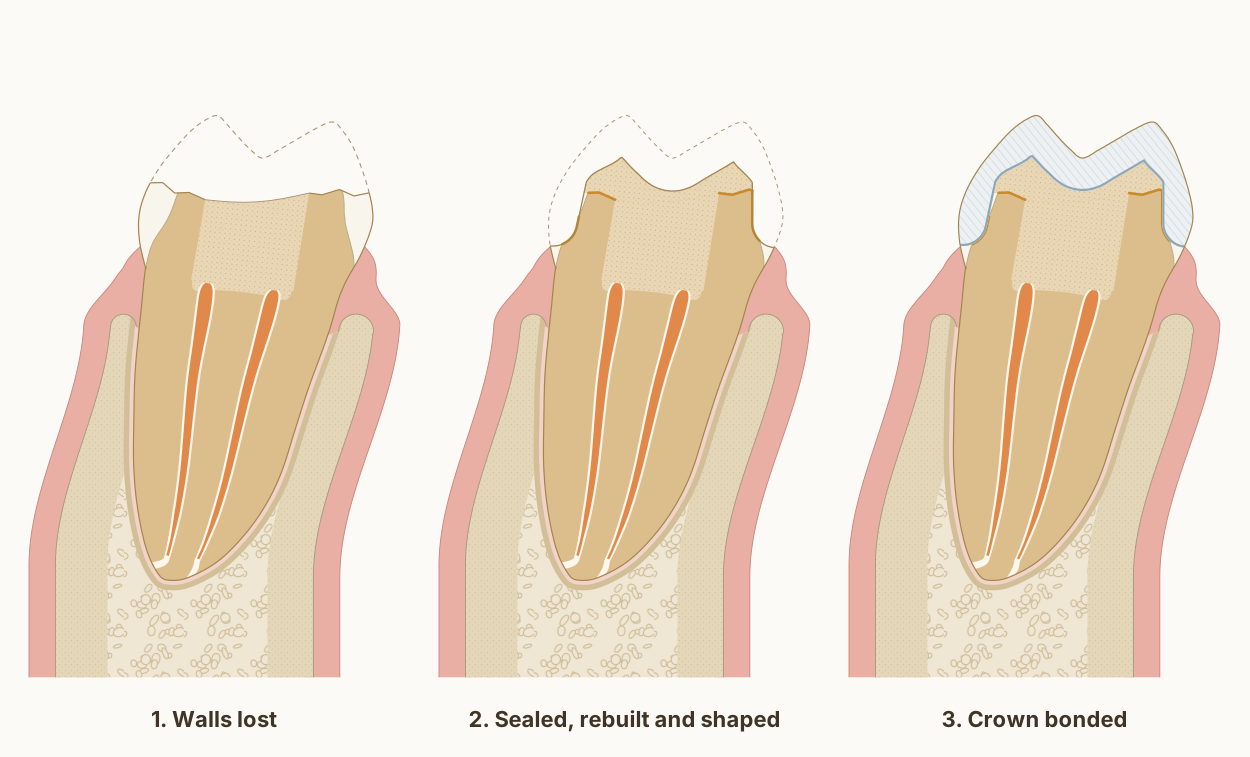
Three stages of a crown on a lower molar after root canal treatment: walls broken away, then the dentine sealed, rebuilt with composite and shaped with a chamfer at the gum line, then a lithium disilicate crown bonded on.

A crown is one of the most useful restorations dentistry has, and one of the most over-prescribed. That is why this practice treats it conservatively, as the last option rather than the default. The right crown on the right tooth is excellent. The right crown on the wrong tooth removes healthy enamel that the patient will never get back.

Dr. Khalid AletaibiWritten by Dr. Khalid Aletaibi, DHA-licensed dentist

QUICK ANSWER

A crown is a custom-made cap that envelops the entire visible portion of a tooth. This is a conservative practice, so a crown here is the last option rather than the default: the smaller, minimally invasive alternatives are assessed first, and a biomimetic partial-coverage restoration is used wherever enough sound tooth remains to carry one. Modern all-ceramic crowns have 5-year survival rates around 95% in current systematic reviews. The question that matters is not how well crowns perform, it is whether your specific tooth needs the full envelopment, or whether a smaller bonded restoration could do the same job while preserving more of the original structure.

Visits

Usually 2

Anaesthetic

Local

Tooth removed

1.5-2 mm all round

Reversibility

Permanent

Longevity

~95% at 5 yrs

What a crown actually does, and what it costs

A crown, which many people call a cap, protects a structurally compromised tooth by enveloping it. That envelopment is genuinely useful: a tooth with a vertical crack, severe bulk loss, or extensively undermined cusps is mechanically held together better by a properly designed crown than by any partial restoration. The benefit is real. So is the cost. To make room for the crown, the dentist removes a circumferential band of enamel and dentine, typically 1.5 to 2 mm of tissue, all the way around. That tissue does not grow back.

Edelhoff and Sorensen quantified exactly how much tooth structure different preparation designs sacrifice [4], and the numbers are sobering, full crowns remove dramatically more tissue than partial coverage restorations on the same tooth. There is also a quieter, longer-term cost: vital teeth that are crowned have a measurable risk of pulpal complications afterwards. The Bergenholtz and Nyman study, now four decades old but still cited because the principle has not changed, documented the rate of pulp necrosis after prosthetic preparation in vital teeth [5]. None of this argues against crowns. It argues against crowning teeth that don't need to be crowned.

The vocabulary around the smaller options is worth knowing, because they are the ones least often named out loud. An inlay sits inside the cusps. An onlay covers one or more cusps and leaves the rest of the tooth untouched. An adhesive onlay, or bonded onlay, is the same restoration described by how it is retained: by the bond rather than by the shape cut into the tooth. A biomimetic crown, where that term is used honestly, means a restoration designed around what remains of the tooth rather than around a standard preparation form. If a plan lists a crown and none of these came up in the conversation, that is a fair thing to ask about.

The same lower first molar in every panel, cut from the cheek side to the tongue side through its front root, with the gum, ligament and bone around it. The tooth and bone are drawn to published measurements; the broken walls, the build-up and the crown show what typically happens, not one patient's tooth.

Diagram page and reuse terms: A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded

Sources and measurements
  • In a systematic review of 7 randomised trials and 1 prospective trial of root-filled teeth followed for at least five years, a ferrule and the remaining cavity walls were the main factors in the survival of the tooth and its restoration, and most studies found no benefit from a post. Naumann et al. 2018, Journal of Endodontics. DOI 1, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • A literature review of laboratory, computer and clinical studies concluded that a ferrule of 1.5 to 2 mm improves the fracture resistance of root-filled teeth, that an incomplete ferrule is better than none, and that where no ferrule can be created at all a poor outcome is very likely. Juloski et al. 2012, Journal of Endodontics. DOI 2, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • A systematic review and meta-analysis of 64 clinical studies, covering 8,051 all-ceramic and 3,509 metal-ceramic single crowns, estimated five-year survival at 98.5 per cent for monolithic lithium disilicate crowns, and found fewer ceramic fractures and chips with monolithic designs than with veneered ones. Pjetursson et al. 2026, The International Journal of Prosthodontics. DOI 3, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • The preparation follows the recommendations an evidence map of 73 articles consolidated for all-ceramic CAD/CAM back-tooth crowns: 1.5 to 2.0 mm of occlusal reduction, a chamfer of at least 1.0 mm, 1.0 to 1.5 mm of axial reduction, 12 degrees of total convergence and rounded internal angles. Deranek et al. 2025, Journal of Dental Education. DOI 4, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • Monolithic lithium disilicate crowns 2.0 mm thick withstood 17 times as many loading cycles in water as 1.0 mm crowns, and 0.5 mm crowns failed at the first; the authors suggest at least 1.5 mm for back-tooth crowns. Dhima et al. 2014, Journal of Prosthodontics, laboratory study. DOI 5, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • Immediate dentine sealing means applying and curing a dentine bonding agent on the freshly cut dentine straight after the preparation, before the impression or scan; a review of more than 30 articles found that it appears to give better bond strength, fewer gaps, less bacterial leakage and less sensitivity. Magne 2005, Journal of Esthetic and Restorative Dentistry, review. DOI 6, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • For glass-ceramics such as lithium disilicate, a systematic review of 83 laboratory studies found that etching with hydrofluoric acid followed by a silane is the most widely accepted surface treatment before a resin cement. Tian et al. 2014, Dental Materials. DOI 7, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • In 160 men followed for 26 years, filling margins placed below the gum line were detrimental to gum and periodontal health; the extra loss of attachment began slowly and could be detected 1 to 3 years after the restorations were placed. Schätzle et al. 2001, Journal of Clinical Periodontology. DOI 8, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • The case and the steps are drawn as Dr. Khalid works: a root-filled molar that has lost its walls, its canals filled as in the site's root canal figure (a single cone in a bioceramic sealer, with composite placed straight over the canal openings); immediate dentine sealing on the freshly cut dentine, then a composite build-up; a chamfer margin at the gum line; and a monolithic lithium disilicate crown, sandblasted, etched with hydrofluoric acid, cleaned with phosphoric acid and primed with silane, then bonded with resin cement under rubber dam. Where the walls broke is illustrative; it is set so that about 2.5 mm of sound tooth remains above the margin.
  • The enamel follows one measured dataset for this tooth, from cone-beam CT of 45 lower first molars: 1.58 mm at the front cheek-side cusp tip and 0.98 mm at the central fossa, its thinnest point. Zhang et al. 2026, BMC Oral Health. DOI 10, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • Two canals in the front root, as drawn, are found in 94.4 per cent of lower first molars, and three in 2.3 per cent, from a systematic review of 41 studies covering 18,781 teeth. de Pablo et al. 2010, Journal of Endodontics. DOI 11, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • Bone level: on cone-beam CT of 100 lower molar sites in 25 adults, the crest of the bone sat 2.03 to 2.11 mm below the enamel edge of first molars, with 1.14 to 1.19 mm of bone over the cheek side of the root near its neck. Othman 2026, The Saudi Dental Journal. DOI 12, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • The cheek-side cortical plate near the crest is drawn from cone-beam CT of lower first and second molars, where it measured 1.1 to 1.4 mm. Sayed et al. 2021, The Saudi Dental Journal. DOI 13, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • Further from the crest, on cone-beam CT of 100 people, between the lower second premolar and first molar: the cheek-side plate measured 1.93 mm at 4 mm below the enamel edge and 2.36 mm at 6 mm, and the tongue-side plate 2.18 and 2.09 mm. Gupta et al. 2025, BMC Oral Health. DOI 14, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • The gum is drawn 1.2 mm thick, within the 0.8 to 1.5 mm measured by ultrasound across lower teeth in 200 periodontally healthy men. Eger, Müller and Heinecke 1996, Journal of Clinical Periodontology. DOI 15, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded
  • The tooth follows the textbook descriptions of a lower first molar rather than a symmetrical outline: the crown leans toward the tongue on its root, the front root's tip lies under the front cheek-side cusp, the roof of the pulp chamber sits at the level of the enamel edge with the floor in the root trunk, and the ligament around the root is drawn 0.2 mm wide, under the quarter of a millimetre the textbooks give, inside a thin lining of compact bone. Wheeler's Dental Anatomy, Physiology and Occlusion, 11th edition, and Woelfel's Dental Anatomy.
  • The roof of the pulp chamber sits at the level of the enamel edge, where it lay in 97 per cent of 100 lower molars measured on radiographs, and the drawing's distance from the cheek-side cusp tip to that roof, 6.36 mm, is the study's mean. Deutsch and Musikant 2004, Journal of Endodontics. DOI 17, A crown for a root-filled tooth that has lost its walls: sealed, rebuilt and bonded

What the longevity data shows

When the indication for a crown is correct, modern crowns perform very well. The Pjetursson group's systematic review of single crowns reported 5-year survival rates in the range of 95% for both zirconia-ceramic and metal-ceramic restorations [1]. The Pieger systematic review focused specifically on lithium disilicate single crowns and reported similarly high clinical success [2]. The most recent meta-analysis of monolithic ceramic restorations confirmed that the move from veneered to monolithic ceramic, driven by chipping problems with veneered zirconia, has produced excellent contemporary survival data [3].

The survival numbers do not, however, answer the question of whether a particular tooth should have been crowned in the first place. A crown that lasts twenty years on a tooth that didn't need it is still a tooth that lost two millimetres of healthy structure. The conservative principle is the same it has always been: pick the smallest restoration that solves the actual mechanical problem.

How I decide whether to crown

The first question is always whether a partial restoration can do the job. If the tooth has at least one or two intact walls, a bonded onlay or large composite can often restore function with a fraction of the tissue cost. The Cochrane review of single crowns versus conventional fillings for the restoration of root-filled teeth concluded there is insufficient evidence to favour routine crowning over a well-placed conventional restoration [6]. That finding has been part of the conservative case against reflexive crowning for over a decade.

When a crown is the right answer, the design choices follow the same conservative logic. I default to lithium disilicate for posterior teeth where strength and aesthetics both matter; high-translucency monolithic zirconia is a reasonable second choice for very high-load situations. Veneered zirconia, with its known chipping risk, is rarely the right call when a monolithic option exists. The preparation is kept as conservative as the indication allows, the margin is placed supragingival or equigingival whenever possible, and the cementation step is treated as adhesive bonding rather than passive seating, which protects the underlying tooth in exactly the way that makes the rest of the restoration's mechanics work.

A close-up of the crown's tongue-side edge, from the same measured molar as the step-by-step figure, with a 1 mm scale. The crown ends on enamel at the gum line, where it can be cleaned and checked, and the gum's attachment to the root below it is left undisturbed.

Diagram page and reuse terms: The crown's edge

Sources and measurements
  • In 160 men followed for 26 years, filling margins placed below the gum line were detrimental to gum and periodontal health; the extra loss of attachment began slowly and could be detected 1 to 3 years after the restorations were placed. Schätzle et al. 2001, Journal of Clinical Periodontology. DOI 1, The crown's edge
  • The 2017 World Workshop replaced the term biologic width with supracrestal tissue attachment, meaning the junctional epithelium and the connective tissue above the bone, and found that restoration margins placed within that connective tissue attachment are associated with inflammation or loss of periodontal support. Jepsen et al. 2018, Journal of Periodontology, consensus report. DOI 2, The crown's edge
  • That attachment has no single width: a systematic review found means of 2.15 to 2.30 mm but a range from 0.2 to 6.73 mm between individuals. Schmidt et al. 2013, Journal of Clinical Periodontology. DOI 3, The crown's edge
  • The preparation follows the recommendations an evidence map of 73 articles consolidated for all-ceramic CAD/CAM back-tooth crowns: 1.5 to 2.0 mm of occlusal reduction, a chamfer of at least 1.0 mm, 1.0 to 1.5 mm of axial reduction, 12 degrees of total convergence and rounded internal angles. Deranek et al. 2025, Journal of Dental Education. DOI 4, The crown's edge
  • For glass-ceramics such as lithium disilicate, a systematic review of 83 laboratory studies found that etching with hydrofluoric acid followed by a silane is the most widely accepted surface treatment before a resin cement. Tian et al. 2014, Dental Materials. DOI 5, The crown's edge
  • Drawn as Dr. Khalid places the margin: at the gum line, on enamel, bonded with resin cement under rubber dam. The cement and the sealing are drawn 0.08 mm thick; both are representative rather than measured.

A close-up where the remaining wall meets the build-up, from the same measured molar as the step-by-step figure, with a 1 mm scale. The freshly cut dentine was sealed straight away, the build-up was bonded over it, and the crown, sandblasted, etched, cleaned and primed with silane, was bonded to both with resin cement.

Diagram page and reuse terms: The bonded joint

Sources and measurements
  • Immediate dentine sealing means applying and curing a dentine bonding agent on the freshly cut dentine straight after the preparation, before the impression or scan; a review of more than 30 articles found that it appears to give better bond strength, fewer gaps, less bacterial leakage and less sensitivity. Magne 2005, Journal of Esthetic and Restorative Dentistry, review. DOI 1, The bonded joint
  • In 15 extracted molars, dentine sealed immediately after preparation bonded at 58.25 MPa, as strongly as dentine bonded directly (55.06 MPa), while dentine sealed only at the cementation visit bonded at 11.58 MPa. Magne et al. 2005, The Journal of Prosthetic Dentistry, laboratory study. DOI 2, The bonded joint
  • For glass-ceramics such as lithium disilicate, a systematic review of 83 laboratory studies found that etching with hydrofluoric acid followed by a silane is the most widely accepted surface treatment before a resin cement. Tian et al. 2014, Dental Materials. DOI 3, The bonded joint
  • A literature review of laboratory, computer and clinical studies concluded that a ferrule of 1.5 to 2 mm improves the fracture resistance of root-filled teeth, that an incomplete ferrule is better than none, and that where no ferrule can be created at all a poor outcome is very likely. Juloski et al. 2012, Journal of Endodontics. DOI 4, The bonded joint
  • In a systematic review of 7 randomised trials and 1 prospective trial of root-filled teeth followed for at least five years, a ferrule and the remaining cavity walls were the main factors in the survival of the tooth and its restoration, and most studies found no benefit from a post. Naumann et al. 2018, Journal of Endodontics. DOI 5, The bonded joint
  • Drawn as Dr. Khalid works: the dentine sealed straight after preparation, then the composite build-up, then the crown sandblasted, etched with hydrofluoric acid, cleaned with phosphoric acid and primed with silane, and bonded with resin cement under rubber dam. The cement and the sealing are drawn 0.08 mm thick; both are representative rather than measured.

Crown vs onlay: how much tooth is covered

Crown vs onlay: how much tooth is covered
Bonded onlayFull crown
What it coversOnly the damaged part of the tooth, keeping the healthy walls.The whole tooth, all the way around.
Healthy tooth removedMinimal; most of the natural crown is preserved.More, because the tooth is reduced on every surface.
How it holdsBonded to enamel and dentine, which reinforces the tooth.Mainly retained by its shape, and often bonded as well.
Best suited toTeeth with healthy walls but a broken or worn cusp or a large old filling.Teeth that are heavily broken down, root treated, or too weak for a partial restoration.
Conservative profileMore conservative; the first choice when the tooth still has good structure.The right choice once too little sound tooth remains for an onlay.

What happens, step by step

  1. 1

    We confirm a crown is truly needed

    First we check whether a smaller bonded restoration could do the same job and keep more of your natural tooth.

  2. 2

    Conservative preparation

    We remove only what is necessary and protect the pulp. The freshly cut dentine is sealed straight away (immediate dentine sealing), then we take a precise digital scan.

  3. 3

    A temporary protects the tooth

    A temporary crown keeps the tooth comfortable while your final ceramic crown is crafted.

  4. 4

    Bonding the final crown

    We fit and adhesively bond the ceramic crown, then fine-tune your bite.

Longevity when a crown is the right choice
All-ceramic crown survival at 5 years[1]95%

Pooled survival from systematic reviews of single crowns. Survival does not answer whether the tooth needed a crown in the first place.

Conservative profile

  • How invasiveHigh
  • Healthy tooth preservedLow
  • Protection for a broken-down toothHigh

COMMON QUESTIONS

What patients ask most.

Do I really need a crown, or is there a smaller option?
It depends on how much sound tooth structure is left and how predictable the function is. If at least one or two cusps and walls are intact, an onlay or large bonded composite is usually the more conservative answer. If the tooth is severely broken down, undermined on multiple cusps, or has a vertical crack reaching deep into the body of the tooth, a crown is often genuinely needed. The decision is made tooth by tooth, not by reflex.
Which crown material is best?
For most posterior teeth, monolithic lithium disilicate offers an excellent balance of strength, aesthetics, and conservative preparation requirements. Monolithic high-translucency zirconia is a strong alternative for high-load situations or where additional strength is needed. Veneered zirconia is rarely the right call because of well-documented chipping problems, and metal-ceramic remains a valid option in specific clinical situations. There is no single 'best', the right material depends on the specific tooth, the bite, and what is opposing it.
How long does a crown last?
In current systematic reviews, well-indicated and well-fabricated single crowns show 5-year survival rates around 95%, with many crowns continuing to function much longer. Long-term survival depends on the patient's bite, oral hygiene, the quality of the underlying tooth structure, and the precision of the cementation step. The crown itself is usually not the failure point, recurrent decay at the margin is. That edge is what your routine visits look after: at your check-up and cleaning, set at 4, 6 or 12 months for you, the margin is checked and cleaned, so early decay there is found while it is still small. What happens at a cleaning is set out in your cleaning, step by step.
Will my tooth feel sensitive after a crown?
Some short-term sensitivity in the first weeks after preparation is normal as the tooth's pulp settles. Persistent sensitivity months later is not normal and is worth investigating, it can indicate an undetected crack, an over-prepared tooth, a bite that needs adjustment, or in some cases an early sign of pulpitis. Crown preparation on vital teeth carries a small but real risk of subsequent pulp necrosis, which is one of the reasons I am cautious about crowning teeth that don't truly need it.
I was told my old crown needs replacing, does it really?
Sometimes, sometimes not. Crowns should be replaced when there is recurrent decay at the margin, a visible fracture in the porcelain that affects function or aesthetics, an open margin that traps plaque, or biological symptoms from the underlying tooth. Replacing a crown purely because it looks 'old' or because a different material is now available sacrifices more tooth structure each time. A second opinion is often the most conservative thing you can do before agreeing to replace an existing crown.
How many appointments are needed for a crown?
Two visits in most cases. The first visit removes any decay or old restoration, prepares the tooth conservatively, takes an impression (digital or analogue), and fits a temporary crown. The laboratory or in-office mill makes the definitive crown. The second visit is the bonded cementation under appropriate isolation. Same-day chairside CAD/CAM is possible for selected cases and reduces the work to a single longer appointment.

Speak to us

Would you prefer we call you?

Leave your name and number and Dr. Khalid's team will call you back to answer your questions and find a time that suits you.

Considering a crown? Get a second opinion first.

Sometimes a crown is genuinely the right answer. Sometimes a smaller bonded restoration can do the same job and save real tooth structure. We'll examine the tooth carefully and tell you what the evidence supports for your situation specifically.

Book a Consultation

← Biomimetic Restorations & Endodontics

Call Dr. Khalid directlyDiscuss your concerns and questions